Showing posts with label placenta sandwich. Show all posts

Monday, January 27, 2014

updated: LOUISIANA IS ABOUT TO CLOSE ITS ABORTION CLINICS AND NO ONE IS TALKING ABOUT IT

EDIT 1/29/14: DATE AND ROOM CHANGE -- the hearing is now TUESDAY, FEB 4 AT 1PM, Room 173. Email fight4RJLA@gmail.com for info or to get more involved.


Oh, Lawd. I am online bright and early to share this news uncovered by some fellow abortioneers in Louisiana. It's scary and needs immediate attention, so please forgive this hasty reblog (from the folks at New Orleans Abortion Fund, with their permission) and take action quickly: show up for the hearing on Wednesday, or write a letter/email for DHH by Tuesday -- see details in purple below.
~~~~~

URGENT: Hearing on "backdoor abortion ban," new clinic regulations in Louisiana

It may not be easy to get excited over 21 pages of Louisiana Department of Health and Hospitals regulations, but you'll want to hear about this!

Just before Thanksgiving, the Louisiana Department of Health and Hospitals (DHH) issued new "emergency" regulations that overhauled the existing regulations on abortion clinics. These 21 pages of rules give DHH the authority to immediately shut down a clinic without opportunity for appeal, even for simple infractions. Clinics have stated that they would be unable to meet the burdensome and excessive requirements, and this would lead to the closure of all five clinics in Louisiana.

DHH's new regulations are another manifestation of the "TRAP" (Targeted Regulation of Abortion Providers) laws that are sweeping the country. They represent an effective ban on abortion, especially for the low-income women that NOAF serves, who cannot afford to travel. Here are some examples of new provisions:
  • Patients must have documented in their charts that hemoglobin and Rh factor lab tests were performed at least 30 days prior to the abortion procedure. This means that some patients will risk being beyond the 20 week deadline in Louisiana (and earlier than that at most clinics) to have an abortion, and will add to the procedure costs for all patients, as they will have to wait an additional month.
  • Each clinic who is applying for a new license must submit a "certificate of need" to the State proving the need for their services. In many other circumstances, such as any change to the location or the ownership of an existing clinic, existing clinics must apply for a brand-new license and (re-)satisfy the certificate of need requirement. The subjective nature of these requirements allows the State to severely restrict new licenses and will provide the State with a mechanism for refusing to allow existing clinics to renew their licenses to operate.
  • There is no right to appeal deficiencies to any unbiased body outside of the Department of Health and Hospitals. Therefore, every deficiency that a clinic is cited with will be allowed to stand, and those deficiencies are often later used to revoke a clinic’s license on the basis of being a “repeat” offender.
  • The new regulations require that all facilities have very specific square footage requirements that are far larger than any currently operating abortion facility. They would be prohibitively expensive to construct, and the requirements have no medical necessity. If the regulations are allowed to go into effect, no clinic will be in compliance on the day the regulations are implemented, and the State will have the ability to shut down every existing abortion clinic in the State.

These regulations were originally enacted without public comment and with no clear indication of need. There will finally be a hearing on Tuesday, February 4 at 1:00pm in Room 173 of the Bienville Building, 628 North 4th Street in Baton Rouge. The New Orleans Abortion Fund and members of allied organizations will be testifying and presenting written comments from advocates, providers, and women who have recently obtained abortions at affected clinics at the public hearing.

The people of Louisiana need your support! Please consider attending this hearing and/or submitting written comments. We have created talking points and a sample letter [PDFs]. Feel free to copy and paste (and re-format if needed!), but please consider adding your personal thoughts.

Hearing details:
Wednesday, January 29, 2014 at 9:30am - get there early; we are packing the place!
Bienville Building, Room 118, 628 North 4th Street, Baton Rouge, LA 70802
NOTE: NOAF and our allies are wearing purple!

If you cannot attend the hearing, we can print and hand-deliver your written comments at the hearing -- you MUST include your full name and address. Email your letter to abortionfundnola@gmail.com by Monday, February3 at 8:00pm CST


Thank you! Together, we can fight back!


Thursday, June 13, 2013

SOS Midwest

Basically.

Midwest abortioneers and others-- did you see this? This Ohio bill will require abortion providers to obtain hospital admitting privileges BUT ALSO specifically prohibit them from making such arrangements with any public hospital or even any doctor employed at one. Funnily enough, in the US the largest operator of non-public hospitals is...the Catholic Church.

Even before these new tighter restrictions are voted on, one Toledo clinic has just closed due to these issues and another is expected to do so soon. You can read more details at the Salon article.

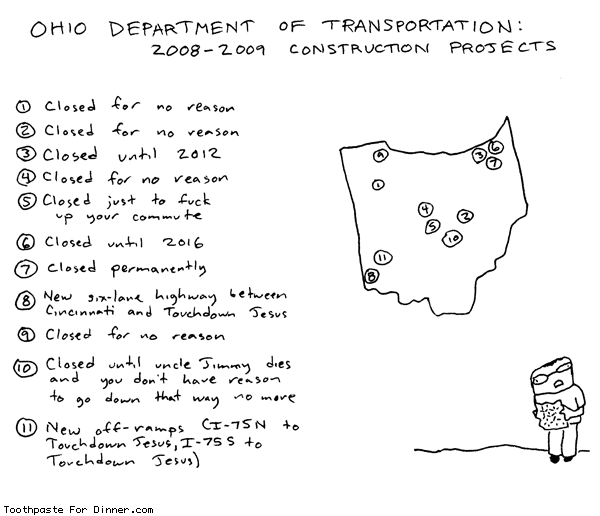
Ohio's provider landscape will look something like this, I guess:


I've been thinking about this issue a lot since the admitting privileges strategy seems to be increasingly popular in the past 1-2 years (and alarmingly effective) in the quest to eliminate providers -- but this is the first state hospital requirement I've seen where state hospitals would be explicitly off-limits in your efforts to comply with the state's hospital requirement. That feels like some next-level, Vonnegut-Kafka-MontyPython type shit (cause I can't decide whether to laugh then cry, or cry then laugh).

If you work in a hospital or ED setting, I want to hear about it: Has the topic of admitting agreements with abortion providers ever arisen in your hospital? And while we're at it, what about emergency treatment for pregnant intakes (including urgent abortion care) more generally?

Images from: The Notebook, Toothpaste for Dinner

Friday, May 10, 2013

My heart needs a break from breaking

Have you been reading the news lately? I have, unfortunately. It feels as though current events have just been an unrelenting stream of examples of the horrors and cruelty that human beings are capable of inflicting on other human beings. Thanks, murderers and abusers and rapists and torturers, but we don't need more examples. We get it. You can stop now.

And in the last several hours I've done only two things: read about the latest awful case of kidnapping and almost-unspeakable abuse, the one in Cleveland, or stewed over it while unsuccessfully attempting to focus on other things.

But I'm here trying to write something because there's a part of me that's sure someone will ask. Or assume. How many hours or days til the half-witted comments hit, ones about how this is all because of the "culture of death" that abortion perpetuates? OR the ones asking why I "care" about this but "don't care" about the trial of Kermit Gosnell, a man who stands accused of killing babies and calling it abortion?

I ask because because it's so, so, so routine; these words have likely been uttered on several prominent anti-abortion blogs today. But I don't want to go find out.

Sometimes, despite being a super-famous internet celebrity (humble joke), and despite bearing the weighty mantle of spokesperson for ALL abortioneers and being asked for comments on ALL bad things that happen to babies or fetuses or embryos (angry joke), a person's got to have some time to themselves to deal with pain.

We often have stuff to say about things that show up in the news, but I'm not interested in being a ripped-from-the-headlines current events commentator. I just wanted to tell my truth, particularly in times when it wasn't represented elsewhere. But you're probably sickened and saddened too, and that's the truth for all of us.

Wednesday, November 7, 2012

Whee! Now Let's Get On With It.


via


Y'all, I am SO RELIEVED. My nerves thank you. Stupid Akin and Mourdock lost their stupid races, and so did stupid Romney. We get to keep expanded health insurance coverage (no pre-existing condition exclusions for me or Desembarazarme!) and copay-free contraception (my neighbor is looking into IUDs as we speak!), we sent many of the frightening rape apologists home, and we don't have to fear uber-conservatives being appointed to the Supreme Court in the next four years (the Arizona 18-week ban is rising through the appeals process right now, eek!).

Note I'm breathing a sigh of relief, not whooping for joy. To me this election represents a pause in the current onslaught -- a shutting-down (ha) of the presumption that anti-choice and anti-justice ideas have momentum -- but not progress in itself. Last night's votes did bring unexpected joy: we got to see several states protect marriage equality (Maine Maryland Minnesota Washington), one state elect the first openly-gay US senator ever (Tammy Baldwin in Wisconsin), and one state elect an all-woman Congressional delegation for the first time ever (New Hampshire). But when it comes to the overall status of reproductive justice, I'm still feeling tentative.

We haven't accomplished progress in one night, but maybe now we can forget about those clowns and their circus and get back to work. I don't want to get TOO excited (GOP-controlled House of Representatives) but maybe Obama really will push for some serious advances now, like progressives have hoped all along, feeling so frustrated. Maybe we'll find a way to expand health insurance to ALL people, maybe EC will be available over-the-counter for everyone (and regular oral contraceptive pills too, please!), maybe provider "conscience" will be taken seriously and will also protect those who conscientiously DO provide, and maybe maybe maybe maybe maybe we can combine all our strength and push someone to do something about the Hyde Amendment (update: hey look, Abortion Gang explains!).

It's time, right?

Now...does anyone want to email Barack?

Otherwise I'm just gonna copy/paste this blog post that I just spitballed, and you'll have the embarrassment of being represented by an email written with way too many parenthetical expressions and words in all-caps. The clock is ticking!

xoxoxoxoxoxo,
Placenta Sandwich

Thursday, October 18, 2012

Guest Post: An Abortion Love Story, Chapter II


Welcome back to Rebecca, a fellow abortioneer who’s agreed to spin us a MOTA (mates of the abortioneers) romance for the ages. You can go back here to read about how they first had "the A-word talk." When you're done with that, read on below for Chapter II, which in my head I've unofficially but fondly titled "My Husband Sleeps With One Eye Open."
~~~~~~~~~~~~~~~~~~~


At first, C didn't really "get" the security factor at work. You know: the protesters. He's European and from a secular country; and he'd lived overseas for years. He wasn't aware abortion was such a contentious issue in the USA because it wasn't in his country. (I also think that because he’s a guy, he probably didn’t pay much attention.)

He was surprised to see all the protesters we'd get sometimes and how they'd harass clients. We were lucky at our clinic -- we didn't have TONS of protesters like many others did -- but he was still shocked to see them.

When we had more than the usual number of crazies out, I didn't like leaving my car at work. The protesters were taking pictures of our license plates; my car was registered to my home address. (I know, I know. Not smart!) I didn’t exactly feel like getting followed. I lived alone in a smallish city and my car was fairly easy to identify.

Early on in our relationship, the clinic was experiencing one of those big protester days, so I asked C picked me up from work so my car wasn't left in our car park all day. As we approached my vehicle, he dropped the car keys. I noticed he took a fraction of a second longer picking up the keys than I thought he would, and that made me a little twitchy. I wasn't sure why.

Later, when I was ranting about protesters, C told me he was concerned about my safety. And then he admitted he had dropped the car keys purposefully .

Why? With his diverse background, including a military history and working in war-torn countries, he had learned certain skills.  It was a trick they used in some of the places he'd been: they'd drop the keys, bend down to get them, and steal a glance under the car to see if there was a bomb.

A car bomb? I was a bit shocked. My first thought was, "That’s not necessary! Nothing like that would happen here!" Yet it was instinctual for him to check.

He explained how surreal it was for him to be so immediately, intimately, acutely impacted by my work: all because of protesters. Part of me was like, "Yeah, well, welcome to our world."

His reaction had been jarring, though. I usually didn't tell family/friends about protester activity or security threats. I didn't want to worry them. Really, I didn't want to deal with their worries on top of mine. They would've told me to quit. This was the first time I saw how security issues at the clinic directly affected someone I cared for. I wonder whether all abortioneers experience that, and how.

Throughout the years, C was vocal about his security concerns. Because of his experience, he didn't think my clinic always took those risks seriously enough. He’d often say he'd do things differently, or thought things like a better alarm system would be a smart move.

He criticized the clinic when they stopped having guards on clinic days, especially when protester activity increased. We lived in the Pacific Northwest where it's pretty normal to carry handguns. The clinic guards regularly pulled guns and knives off guys.

It was hard for me to listen without feeling defensive and thinking he wasn't critical, really, underneath it all, about abortion, about my job, about work that I loved.

I now understand that wasn't the case: he was just genuinely worried sometimes. Which is a shame. It's a shame we have to work in conditions, in the United States, where our family worries about us because of some crazies. Have you had similar experiences?

Thursday, September 27, 2012

Guest Post: An Abortion Love Story

Please give a warm bloggy welcome to Rebecca, a fellow abortioneer who’s agreed to spin us a MOTA (mates of the abortioneers) romance for the ages. Consider this Chapter I of the story of Rebecca and her husband C. I can't wait to read more. 
~~~~~~~~~~~~~~~~~~~


I can’t remember how I first told him I worked at an abortion clinic. We met online, which was sort-of new territory 10 years ago. I had this rule that I wouldn’t meet anyone in person unless they were pro-choice. We’d talk online and on the phone, I’d gauge how liberal they were, ask lots of leading questions, then pop the big one: “are you pro-choice?”

Even if a guy told me he was pro-choice, I’d still wonder how pro-choice he was. Wonder if he was pro-choice enough to handle me working at a clinic. So I’m sure C and I had an initial discussion about abortion, but I doubt I immediately told him I worked at the clinic.

Isn't it strange that I don't remember the first time I mentioned my abortion work to my husband? I must've told him very soon after meeting him, though, because he came home with me the first day we met...and I had clinic the following day! Ha.

Here’s something interesting. I just asked C if he remembered when I “outed” myself to him about working in a clinic. He doesn’t. He thinks that tells a lot about his feelings/thoughts about abortion: it wasn’t a big deal to him, he just admired the work.

He also wants me to point out that he wasn’t exactly a typical guy (that’s for sure!). He’s not American, and he had been doing overseas development work in emergency situations. So he was aware of the consequences of unsafe abortion in developing countries. Providing safe abortion, from his perspective, was a no-brainer. He remembers we did discuss my interest in women’s global rights and health, so that all tied in to the big abortion reveal convo…Which wasn’t a big deal after all.

So, C was traveling around the USA when we met. He had been on the Afghan/Pakistan border during 9/11 and got a little burned out from doing aid work. He wanted to be in a country with smooth pavement, clean water, and good food. Within a week of arriving in the States, he was hanging out at my house.

One evening, I came home from a long day at clinic, feeling exhausted. It was one of those days where you felt emotionally drained afterwards. Well, more than usual. We were having protester issues, to complicate matters. I couldn’t wait to open my apartment door, get a huge mug of tea, and fill up the bathtub. This was my ritual: soak in the bath for ages, read a book, then make phone calls from the tub and talk. I lived alone and it's how I relaxed after work, decompressed from work. How I tried to leave work at work.

So that’s exactly what I did. I didn’t stop to hang out, say hello, or have a chat with C. Just went straight into the bathroom to run the bath. C didn’t know me well enough to realize this was my usual routine. And I didn’t realize it needed explaining!

You can see where this is going.

C was left wondering if he had upset me, had overstayed his welcome – if I was sick of him being around. It made him very uncomfortable and he asked if I wanted him to leave!

That wasn’t the case at all, of course. But I realized I had to communicate about my needs, about how I had to take care of myself, especially after a really stressful clinic day. Obviously this work can be very stressful at times. I had to learn to become aware of my ways of taking care of myself and how they might impact my partner. That was new for me, and a first step in the gradual intertwining of our lives.

Wednesday, August 1, 2012

Bad Freaking News, with helpful annotations

AZ Abortion Law to Take Effect After Judge's Ruling
Mon, Jul 30 2012, Reuters

Arizona's law banning abortions after 20 weeks will go forward, says U.S. District Judge James Teilborg.

The law is a change from the current system in Arizona. Under the previous law, abortions were permitted up until viability which occurs around 24 weeks. Starting Thursday, abortions after 20 weeks will not be allowed unless there is a medical emergency.

Judge Teilborg was asked to stop enforcement of a new Arizona law passed by the legislature. He declined to do so by ruling that the law is acceptable under the Constitution.

Arizona is not the first state to ban abortions around 20 weeks but it's still a tricky decision, legally speaking, for a state to ban abortions before viability. The Judge acknowledged that the Supreme Court has blocked states from implementing outright bans on abortion before viability as an unfair burden [but he says that] the Arizona law is acceptable in part because it doesn't impose much of a burden on a pregnant woman.

His reasoning is that there is relatively little time between 20 weeks and the 22-24 weeks when viability occurs,
[1][2] according to Arizona Daily Star.

Part of the burden on women in pre-viability abortions is that they may not know of fetal abnormalities before that time. The evidence presented to Judge Teilborg indicated that there are few conditions that would be diagnosed after 20 weeks that could not have been diagnosed earlier.[3] As a result, banning abortions after 20 weeks would not significantly increase the burden on the woman.[4]

He did note that if a unique circumstance arose where fetal abnormality was diagnosed after the first 20 weeks, it would be appropriate to challenge Arizona's abortion law.[5][6] But until that actually happens, the typical situation will dictate the constitutionality of the law.

To uphold a restriction on abortion, the state must also show a legitimate reason for the new restriction. Teilborg was convinced that the state's respect for life[7] and concern for preventing fetal pain[8] was a sufficient concern to justify the law, reports Arizona Daily Star.

Arizona's new abortion law is not the first of its kind, although it may be the first law banning abortions after 20 weeks to be challenged in federal court, reports Reuters. The plaintiffs had not filed an appeal as of Monday.


Footnotes, placenta sandwich 08/01/12:

[1] More like 24-26 weeks; it would be ludicrous to use 22 weeks as a general theoretical threshold for viability, even in a high-tech, high-cost US hospital context.


[2] (Also, how is 4 weeks just a "little time" to be cutting off? Is it really? What did he base this on? Has he experienced a crisis pregnancy before? I'm honestly curious what makes a person decide this rather than something else. Because for every person talking about banning later abortions who calls 4 weeks "relatively little time" [as in, "I don't really understand your life, but a couple weeks' less time is not a big deal, just get to the clinic earlier"], there's another person talking about banning later abortions who calls 4 weeks "plenty of time" to find out you're pregnant, decide what you're going to do, and seek out the necessary care [as in, "I don't really understand reproductive biology, but you're already 8 weeks pregnant, what took you 8 whole weeks to get an abortion?"]. Somehow, they're both wrong.)


[3] I don't know what evidence this refers to, as there is plenty of time past 20 weeks for plenty of fetal development to go wrong, and it does.


[4] Few conditions are undetectable before 20 weeks, and "as a result" it wouldn't be burdensome to ban abortion after 20 weeks? Wow, so many people are erased in that one little phrase. Including women who are seeking later abortions for reasons other than fetal anomaly.


[5] Sad but true. Assuming this ruling isn't overturned, the last hope for people needing abortion care in Arizona is for an already-pregnant person to be adversely affected by this ban and have the means to bring their specific case to court. Of course, as in Roe v. Wade, the individual adversely affected will be well past their pregnancy by the time of the court's decision -- which sometimes results in a judge saying that the claimant is no longer affected and thus no longer has standing! Isn't this the original meaning of "Catch 22"?


[6] But also, why is it that the only person hypothesized to have standing as an adversely-affected party is a woman whose pregnancy was diagnosed with a fetal anomaly after 20 weeks? What about those who face other kinds of situations and obstacles in obtaining their abortion care before 20 weeks (see footnote [3])?


[7] Not WOMEN'S lives, silly!


[8] We don't know when a fetus is capable of experiencing pain, but it's definitely not at 20 weeks. In fact, it's not anytime before 27 weeks and it may be even later. This is the general consensus of embryologists, neonatologists, neurologists and other people knowledgeable about the development of the nervous system.

Thursday, July 5, 2012

The Great Macy's Fourth of July Abortion Sale: Get 'em while you can! (offer valid only in Mississippi until 7/11/2012)

This is actually a breadline, not a bank run or a premodern Black Friday. But when I thought about it, the breadline matched the vibe of the clinic waiting room better than those. People are there -- with their spouse, mom, kid, infant -- because they really need to be. 


So...

Remember my last post, where I was kinda sick and tired of legislators playing doctor (and not in the sexy way) (but also, is playing doctor actually sexy to anyone?), and I was writing about the last abortion clinic in Mississippi being legislated out of existence, and about Rep. Bubba Carpenter, and how he was talking in what I imagine is a too-bad-so-sad wah-wah voice about how the other side talks way too much about "some poor pitiful women" who might risk their health and lives trying to end their pregnancies by any means available, and I think I might have blacked out shortly after that as an internal defense mechanism?

Yeah, I know: oof. But let's talk about Mississippi some more!

So the bill passed and was signed by the governor and its stipulations include that abortion providers must have hospital admitting privileges -- something Bubba Carpenter noted was notoriously difficult for anyone to obtain, not just abortion providers -- and that means that this last clinic in Mississippi, which has not been able to secure admitting privileges, will have to close. But then, since as Bubba Carpenter noted this law is not trying that hard to be constitutional, a judge stayed the new law until a court hearing planned for July 11 -- giving the clinic a reprieve of, uh, about a week.

And here's something that interests me as an abortioneer.
But it has also created a rush of women from across Mississippi wanting to have abortions. The clinic's three doctors normally perform about 40 abortions a week, but received more than 100 calls in one day last week from women trying to schedule appointments. Two of the doctors live out of state and will fly in to perform abortions this week, said Diane Derzis, the clinic owner.

"What women are hearing is, You may not be able to have an abortion soon," she said. "If you're pregnant and you don’t want to be, you’re thinking, 'By God, I've got to get in there fast.'"
Seems kind of weird, doesn't it? Like a run on the banks, as my arm candy quipped. You'd think that the need for abortion care is pretty much static over the course of a year, since pregnancy can occur in any season and any abortion clinic is the potential provider for at least several million people of reproductive capacity. But demand for services really does seem to have a certain flux to it. While I can't remember hearing of a run on the clinics (though I guess it's not hard to understand), I have noticed other ups and downs and maybe patterns.

I've mentioned before that I had many clients who were able to finally secure their abortion care when their tax refund came back -- and even some who specifically filed early in order to make sure they raised enough money before they reached 12 weeks when the fee would start progressively increasing. Those patients were very resourceful and very on top of it. And I sympathized with their certainty that they made little enough to be owed a refund -- my full-time job qualified me for both a tax refund and assistance from an emergency abortion fund should I ever need it.

But demand also seems to drop on holidays, especially big ones. It's hard to seek an appointment while hosting extended family, driving to grandma's, juggling your parents' or grown children's multiple Thanksgivings after a divorce, entertaining your school-aged kids at home, or arguing with your teenager about sharing the family car over winter break. You don't have as much privacy, time, or energy for taking care of yourself. Shit's hectic.

Then, weeks after a holiday, demand bounces back to levels even higher than before. Phones ring off the hook at the emergency abortion fund, they ring all day although you have multiple phone lines and someone answering every line. Same thing happening at the clinic, which is also jam-packed with people -- you have to bring more chairs into the waiting room -- and clients want to know what is the point of making an appointment if you still have to wait all damn day. (The answer is you struggle with turning people away from care, and wish there was such a thing as walk-in care, but in your state there's a law requiring advance appointments so pregnant people can take time to "cool off" and think hard about their impulsive and flighty decisions. As Sarah Silverman says, maybe they're not as hungry as they think they are.)

I say "weeks" after a holiday but we'd often remark that it seemed to be about four to six weeks after a holiday. Kind of joking, because that's how long it takes from fertilization (four) or last normal menstrual period (six) to the earliest point in pregnancy that most clinics are able to offer abortion care. Kind of not joking, because it really happened. At least three years I noticed that after a December-January lull, we'd have the most insane February and March. That's the time of year that I first became an abortioneer, actually. At first I thought that was just how it was -- that we'd have 100 appointments per day forever. (On the plus side, a lot of those were double-bookings or ambivalent patients who ended up going to another clinic for prenatal or abortion care. We didn't actually check that many patients in per day.)

I could surmise that stereotypically hectic and overburdened times (Thanksgiving/Christmas) or stereotypically romantic times (New Year's/Valentine's) or stereotypically hedonistic times (spring break, New Year's again) lead to unintended pregnancy. And surely the delaying of one's own needs during family-heavy holidays would explain part of the resurgence of appointment requests afterward. But I don't really know and I don't think there's any way to find out on a large scale. It'd be interesting, though, to ask individual women to recount the story of what prompted them to seek abortion care when they did, and why. If only such questions weren't so politically loaded, so likely to suggest there's a right and a wrong answer, maybe we'd hear a lot of honest and interesting stories.

Wednesday, July 4, 2012

Some days I can't bear to look


I know I haven't been around much. Frankly, keeping up with the insane and nonstop political assaults on abortion and related care has been nearly too much to bear. You'd think I'd be writing nonstop, because SO MANY FEELINGS, but at times the feelings kinda drain my emotional energy. I know some of my co-bloggers have been feeling that same drain, lately, in various ways -- and I bet fellow abortioneers in the field have, too.

So it seems almost futile to single out one law and one group of politicians. But if any law has earned that, I guess it'd be the latest restriction out of the magnolia state. Mississippi, come on down!

Maybe you've heard? The lawmakers who passed Mississippi's House Bill 1390, while claiming to be motivated by a desire to protect women from dangerous abortion providers, are also cheering the fact that the bill will have the effect of shutting down the only existing legal abortion provider in the state.
Sen. Kenny Wayne Jones (D-Canton) asked Sen. Dean Kirby (R-Pearl), who chairs the Senate Public Health Committee*, whether ending abortions in the state would force women to resort to dangerous, back-alley abortions.

"That's what we're trying to stop here, the coat-hanger abortions," Kirby replied, in reference to the abortions provided at the clinic in Jackson. "The purpose of this bill is to stop back-room abortions."
*I would also like to call your attention to the fact that Sen. Dean Kirby chairs the Senate Public Health Committee. Presumably, that is a Senate committee on public health. But maybe it's...a Senate committee against public health? I guess the title isn't super specific.

Oh, speaking of the Legislative Brotherhood Against Public Health, see also the breathtakingly cavalier Rep. Bubba Carpenter announcing afterward:
"We have literally stopped abortion in the state of Mississippi. Three blocks from the Capitol sits the only abortion clinic in the state of Mississippi. A bill was drafted. It said, if you would perform an abortion in the state of Mississippi, you must be a certified OB/GYN and you must have admitting privileges to a hospital. Anybody here in the medical field knows how hard it is to get admitting privileges to a hospital.

"It's going to be challenged, of course, in the Supreme Court and all -- but literally, we stopped abortion in the state of Mississippi, legally, without having to-- Roe vs. Wade. So we've done that. I was proud of it. The governor signed it into law. And of course, there you have the other side. They're like, 'Well, the poor pitiful women that can't afford to go out of state are just going to start doing them at home with a coat hanger.' That's what we've heard over and over and over.

But hey, you have to have moral values."
Wow. Was that a sneer I just heard? And then...a shrug?

He has a point, right? Sure there might be some poor pitiful women who can't afford to go out of state for their medical care and end up injured or dead using coat hangers and home remedies -- but aren't we pro-choice people (the other side) just talking about those women to score political points? I mean, why else would you bother talking about them? We say it over and over and over because we don't have better talking points, I guess. But hey! Those deaths are so trivial we can mock them and the people who talk about them.

(Later, Rep. Carpenter also shrugged off his coat hanger 'quote' as "just some language that some of the African-Americans used.")

(You thought I made up that last bit, didn't you? But no. He really did. I mean, it sounds like he's saying that therefore those accounts amount to nothing worth examining? But hey! That's okay, because African-American women (and other black women, and other women of color) definitely don't have even more experience with unsafe abortion than white women.)

Gosh, wonder why I feel so tired?

Thursday, May 31, 2012

An anniversary of a loss


Somehow it's already May 31 again. It's my sibling's twentieth birthday, and it's the third anniversary of Dr. George Tiller's murder by a "pro-life" gunman. It'd be hard to forget this day.

More than one of my colleagues have told me that brilliant blue-sky almost-summer days still remind them of the afternoon we learned Dr. Tiller was gone. It was a Sunday, the Sunday after Memorial Day, and every Memorial Day since then I've thought about Dr. Tiller, who was an Air Force pilot, but who lost his life decades later for being a doctor. "Our veterans died so you could have those freedoms." Except, for once, it's true.

It'd be hard to forget this day, but it's also difficult to remember it. Remembering sets me to wondering how many more years we'll remember to honor Dr. Tiller, and also whether anyone outside abortionland remembers anymore, or cares.

Remember? Remember how our president gave speeches shortly thereafter about finding "common ground" on abortion? Don't you wonder where, exactly, that common ground is? Is it on "Let's come to a compromise on how many healthcare providers you assassinate per year"? In the wake of a Southern string of 3 targeted burglaries at clinics and 3 women's health buildings set aflame (some of which don't even provide abortion care), wouldn't you really like to know what common ground looks like? "Let's agree that no one likes fires in the summer; you could at least save arson for the winter months"?

Where's a libertarian declaring "Those who would trade liberty for security..." when you could actually use one?

Dr. Tiller didn't fuck around like that. They massed outside his office, and he had a huge sign printed: "Women need abortions, and I'm going to provide them." No mincing, no equivocating, and no compromising his patients' care. He went to work every day to protect women's freedoms. Someone shot him in both arms, and he went back to work the next day. He had a gate at the clinic and wore a bulletproof vest -- but his murderer shot him in the head, at church. As you know, freedom ain't free, and that's why we as a society support our abortion providers LOL naw jk that would be crazy.

Monday, April 30, 2012

Guest post: TRANSVAGINAL ULTRASOUNDS! Or How We Missed the Real Story in Virginia

If you work in any field related to abortion, you probably remember that our so-called "win" in the battle over Virginia's ultrasound bill was actually somewhat horrifying. But Amy Littlefield's telling of that story is among the best I've seen, so and she's graciously shared it with us here. You can also catch the original at her beautiful new site for the Provider Project.

~~~~~~~~~~~~~~~~~~~~~


TRANSVAGINAL ULTRASOUNDS! Or How We Missed the Real Story in Virginia


To demonstrate why we need stories from abortion care workers in the struggle for reproductive justice, I want to share a little story about an recent legislative attack you may remember...

A couple months ago, some legislators in Virginia decided to pass a law mandating ultrasounds for women seeking abortions. Their thinking seemed to center on a few monkey-brained assumptions:

1. Women seeking abortions may not realize they’re pregnant until they have an ultrasound.

2. After viewing a blurry, black-and-white blob, women will become so overcome with motherly emotions that their financial/logistical/emotional/spiritual reasons for seeking abortion will disappear.

3. Women can’t make decisions for themselves. Legislators should make decisions for them.

4. People who know nothing about medicine are qualified to dictate medical policy.

The legislators might have benefited from speaking to someone in abortion care who had a basic grasp of what happens between providers and patients. If they did, they might have realized:

1. Most women seeking abortion realize they are pregnant.

2. Ultrasounds are routinely provided as part of abortion care.

3. The level of detail required of the ultrasound image would mandate a TRANSVAGINAL ULTRASOUND for many women in early pregnancy.

Then something glorious happened. People who had a basic grasp of medical knowledge noticed that the law would require a specific medical procedure that involved putting.something.potentially.unecessary.into.my.vagina. The rage of the feminist community was unleashed upon Virginia. More than a thousand people protested outside the State Capitol and some were arrested. The word “vagina” was EVERYWHERE.

“Transvaginal,” said the TV anchors.

“Vaginal probe,” agreed the newspapers.

“Holy crap!” said those of us unaccustomed to seeing the word “vagina” in such places.

Many decried the bill as state-sponsored rape. Here, the feminist community may also have benefited from the wisdom of abortion care workers, who might have noted that transvaginal ultrasounds are in fact a routine medical practice that clinics often use to accurately diagnose gestational age.

Some in the world of abortion care worried that patients might come to see all transvaginal ultrasounds as rape. Others hoped patients would understand it was the legislative force -- not the actual probe itself -- that was a violation of will. For the most part, these voices were drowned out by sound bites.

The outcry forced Governor Bob McDonnell and the Republican legislators to back down, instead passing a watered-down version of the bill that required an abdominal ultrasound and the offer of a TRANSVAGINAL one.

But the debate ignored another key provision of the Virginia law -- one that many in abortion care believed would far more dramatically impact the lives of women seeking abortions. The bill required a waiting period between the ultrasound appointment and the abortion -- you know, so women could get a good hard look at that fuzzy, black-and-white picture. Women who lived within 100 miles of the clinic would need to wait 24 hours. Those who lived more than 100 miles away would need to wait two hours.


I spoke to Rosemary Codding, Director of Patient Services at Falls Church Healthcare Center in Virginia. She suggested it was the waiting period that worried her most, not the transvaginal ultrasound requirement. For many patients it meant two days of childcare, two days off from work. Some women would need to wait a week between the ultrasound and the abortion because of their schedules, meaning the clinic’s diagnostic ultrasound -- you know, the one with an actual medical purpose -- would need to be repeated. Insurance companies bill patients every time they walk in the door, so it would mean two co-pays at least -- or even more for women without insurance.

“If you’re 99 miles away, you’re looking at a 200-mile drive,” she told me.

But the workers at this clinic in Virginia hardly had time to worry about this law, she went on. Because Virginia had passed a series of onerous TRAP laws, part of a nationwide effort by anti-choicers aimed at stopping abortion by imposing ridiculous requirements on things like the size of a clinic’s janitor’s closet. I’m serious about that. That’s not a joke. The janitor’s closet is actually part of this law.

“We have a very nice janitor’s closet that is really well-organized,” sighed Codding.

The law requires things like eight-foot-wide hallways and a cavernous size for surgical rooms, she said. Already, thousands of dollars had been spent determining whether the clinic could come into compliance with the law -- or whether they would need to close.

The ultrasound mandate was an outrage, yes, but it was only one of many threats faced by providers in Virginia. And unlike the issue of TRANSVAGINAL ULTRASOUNDS, the TRAP law received little coverage by the mainstream media.

And that is why I believe we need to listen to the stories of abortioneers. As we face unprecedented attacks on women’s access to abortion, we need to be informed about what a TRANSVAGINAL ULTRASOUND actually is and when it is necessary. We need to know the impact laws will have on the ground -- not just in theory, but in practice. When we listen, we may come to understand the situation is far more complicated -- and far more urgent -- than we may have imagined.

Thursday, April 12, 2012

Ask Aunt ABby: the morning-after STD test


Time: Surprisingly complicated!

Spring has sprung here at Abortioneers HQ, and there's a new feature on the block! You've got questions. We've got answers. And we received a comment that may or may not deserve its own post.

After reading VV's post on the importance of Backing Up Your Birth Control, Virginia commented:
So much concern about getting pregnant and been able to terminate it...what about getting HIV and STDs while having unprotected sex, do you go check if you got those as fast as you go get a day after pill??


Dear Virginia,

It's hard to tell if you're being snarky or simply not very knowledgeable. Either way, welcome to our new advice column, and thanks for giving us an opportunity to clear up potential misconceptions!

Testing for STIs the morning after unprotected sex (especially HIV, which can take up to 6 months to be detectable) is like testing for pregnancy the morning after unprotected sex -- you won't get a positive result when you test that soon, even though you're not in the clear. So to directly answer your question: No, of course you don't "go check if you got those as fast as you go get a day after pill" [AKA the morning-after pill, emergency contraception, EC, the brand-name Plan B, or any number of generic-label names], as you put it. You literally CAN'T do it right away; whereas with the morning-after pill, you MUST.

That's why, instead of rushing out for a meaningless "morning-after HIV test," many people make it a habit to seek testing at regular intervals. I usually do mine at my yearly physical, because I consider it part of a complete checkup. Many providers suggest you only need to test when exposure is suspected, for example IF you had unprotected sex in the past 6 months or year and haven't yet had a test in that time.

Contraception, on the other hand, is important to seek out as soon as possible after unprotected sex, in order to prevent ovulation -- because that's how ALL birth control pills work, including emergency contraception. The longer you delay, the more time for ovulation to occur, and if it does, then EC won't work and you're left at risk for pregnancy. (This is why taking a regular birth control daily is still most effective -- you've targeted ovulation BEFORE the approach of sperm even begins.) If you miss that window and one of your ovaries does release an egg into its fallopian tube, then at that point all you can do is wait a couple weeks to see if a pregnancy does result, and if so, then (potentially) seek abortion care.

It's important to realize that the "morning after pill" is NOT the same as "getting pregnant and be[ing] able to terminate it." You can only use the morning-after pill to PREVENT pregnancy, and it's only effective in the first 5 days after unprotected sex; abortion, on the other hand, can only take place AFTER pregnancy has begun.

I sure do hope this helps, Virginia. Feel free to follow up with lingering questions, and definitely feel free to share this knowledge with your friends and family.

Yours,

Placenta Sandwich
VP of Taking You At Face Value
Head Know-It-All
Abortioneers

Friday, March 30, 2012

Crushed

You guys, it passed. I really don't know what to say, do, feel. Much less what my colleagues in Georgia are feeling. Please give me a couple days to find my words :(

Thanks, as always, to those of you who spread the word or contacted state representatives in Georgia.

Tuesday, March 27, 2012

Tuesday night homework: please help Georgia!


Can't you see my crazy eyes? Don't make me a law! 

Friends, readers, countrypersons: lend me your eyeballs! I have an important piece of evening reading for you, followed by a super-quick writing assignment. Scroll down if you want to skip my navel-gazing and discover your mission.

[COMMENCE NAVEL-GAZING]

Lately I've been feeling like I can't even keep up with the onslaught of legislation designed to prevent would-be abortion patients from getting the care they need and to make their providers give up, board up the clinic and retire or something.

Not tryna brag, but in previous years I was pretty damn knowledgeable about the status of abortion legislation, regulation and jurisprudence at the federal level and in most states. If you asked me about a state-level bill I could usually tell you what its language really meant or what stage in the legislative process it had reached so far or what its practical implications might be.

This year, though? This year, if you told me "I saw on facebook that Hawaii is going to require married women to get a permission slip signed by their mother and their boss and then wait 7 to 10 business days before having an abortion," well idunno, maybe they are! Who am I to say, "No way, no way would lawmakers ever try to do something so awful and insane"? Recent evidence points to the contrary!

Honestly, it was difficult just now to dream up an example that's plainly absurd, because real-life happenings have been so goddamn absurd. But when a bill becomes law, whether or not it is too crazy to exist doesn't matter -- because suddenly it does exist, period. Suddenly you can't get the care you need. Suddenly your doctor has to decide between following her duty to care for her patients' needs, or obeying a law she knows is unjust.

That moment when the laughably absurd bill becomes the terrifyingly absurd reality has happened to me before, most starkly in 2006 when the Supreme Court decided Gonzales v. Carhart. The ruling allowed Congress's so-called Partial Birth Abortion Ban Act to take effect, via an unprecedentedly patronizing position on the part of Justice Kennedy that the government has an interest in protecting "mothers" (any pregnant person) from making decisions they might "come to regret." On the day of that ruling, I was at work, speaking with a woman whose baby was dying in utero; she asked if it was possible to remove the fetus relatively intact so she and her husband could hold it and "say goodbye." I found myself telling that woman, and others like her later, that we could not attempt to honor her request because Congress had just outlawed it. Your representative called; he says to tell you tough titties, crybaby.

[END NAVEL-GAZING]

Those terrible moments will happen again and again unless we refuse to feel helpless and instead move to take action. Your assignment is to foment urgent last-minute opposition to Georgia HB 954, yet another insane proposal to outlaw certain abortions. Georgia has seen and defeated similar bills in past years; but this one has gotten quite far in the legislative process -- meaning it's in grave danger of passing.

I once lived in Georgia. I still feel a strong connection to it, and I really hate that it feels like the rest of the country considers Georgia a lost cause when it comes to rights and liberties, or thinks such legislation won't make that much of a difference for that many women. They're wrong. Many people don't know this, but Georgia has several providers who currently care for patients with later pregnancies and patients with severe or complicated health conditions. Without appropriate providers in Georgia, these patients would have to travel clear across the country or receive care in less well-equipped facilities.

There are three days left to the legislative session, and that's when the crazy backdoor shit goes down. If you have any connection to Georgia, please contact the state representative in your area and ask them to OPPOSE HB 954; if you have no connection to Georgia, please spread the word to others ASAP.

Here's the update (and news item clarification) that I received today from the organizers on the ground with Planned Parenthood Southeast:
Today, the Atlanta Journal Constitution covered the bill in an irresponsible piece of reporting and on the front page no less. Contrary to the story, last night the bill was not stripped and was not killed for the session. The bill is not based on sound science and seeks to intrude on the doctor-patient relationship of women facing some of the most difficult medical circumstances. 
Among other things, here's what's still wrong with HB 954:
  • The bill is still unconstitutional. It still has only a narrow health exception and includes no exception for the mental health of the mother.
  • The bill still requires the physician to use the method most likely to save the life of the unborn child even if that method causes health risks to the mother.
  • The bill still includes no exception for rape or incest.
We know all too well that it isn't over until it's over when it comes to the General Assembly. Session ends on March 29, and we need to keep up the pressure to ensure that private medical decisions are left to a woman and her doctor.


Lawmakers need to look at how similar bills have impacted women in other state and understand that Georgia women deserve better. This bill is an example of the level of government intrusion that takes place in women's health care and we need to let our legislators know that we've had enough. Contact your senator now. Tell them you've had enough of their lack of concern for victims of rape or incest, their intrusion into how doctors practice medicine and their intrusion into women's lives.

UPDATE: Good news, but don't exhale yet! The bill appears to have died after revision by the Senate...because Republican House members refused to accept the addition of an exception for women with "medically futile" pregnancies (i.e. dead or dying fetuses). In other words, House members remain committed to a no-exceptions ban -- and there are 48 hours left in the session for them to try to revive one. A few years ago, this was more than enough time for them to pass a last-minute mandatory-ultrasound law right under everyone's noses. PLEASE stay on top of this until the session is officially over.

Thursday, March 1, 2012

The story of the time I was a dick


Why does she keep shouting ABORTION at me? 

Yesterday our guest blogger Amy mentioned that phone calls about abortion care often sound like this:

"Um...I wanted to know how much it costs?" and "Hi...I'm looking for some information about...abortion?" (spoken as a question, with the word "abortion" issued in a whisper)

And that her responses sometimes sounded like this:

"I would be happy to answer any questions you have about ABORTION! What type of ABORTION do you think you might be interested in having?"

I can totally relate. Who hasn't had this kind of call? It was one of the first patterns I noticed about callers when I started working on the phone lines.

Maybe Amy was more mature or less self-centered than me when she started her clinic work. But for my part, there was a real evolution in how I understood such callers. Initially, I felt frustrated to pick up the phone at my work and hear that the person on the other end of the line couldn't bring themselves to speak about my work. I experienced it as stigmatizing of ME, like they were attempting to distance themselves from my work even as they were asking me to tell them about it.

Sometimes they would ask with words like "terminations" or "D&C" instead of "abortion" -- maybe those words sounded more genteel or more like medicalese.

I'm ashamed to say that, early on, if someone called and said, "Hi, I need to know how much it costs," I would reply, "For what kind of services?" Even though it soon became clear that, if someone was calling about, say, a Pap smear, they simply said "Hi, I need to know how much a Pap smear costs." For a brief period of time, I believed that it was more important for the caller to say the word abortion than to feel comfortable asking about it.

At least that phase ended rather quickly. When a woman called and I heard echoes as she asked me questions, I mentioned her voice was sounding funny, as though she was in a bathroom or something -- and she said yes, she was at work and this was the only private place she could duck into. Duh, me.

Whether because they're not sure they've called the right place, they can't believe they're in this situation, or they can't risk being overheard by a coworker or family member, callers can't always discuss abortion openly and explicitly over the phone.

There will be time for that at their appointment, if they make one, when they meet with the counselor or health educator to express any questions or concerns about their health, the procedure itself, their experiences leading up to the appointment and how they will fare afterward. Usually patients can bring a loved one or support person into the counseling/education session, but a portion is also dedicated to one-on-one time with the staff person, in case the patient has something that might not be easy or safe to express in front of their companion. These sessions can be conducted as part of an abortion appointment, or prior to deciding whether or not to have an abortion. It's dramatically different from a phone call that might by necessity be taking place in public.

So now I know better. I learned to respond to "I need to know how much you charge" with something like, "Sure, I can talk to you about our different fees, but we provide many kinds of care here. Were you asking about a Pap smear, or...an abortion, or...?" If they are asking about an abortion, they normally stop me there and say "Yes, that's it." Easy peasy. It's okay for me to do the talking, if that's what the caller is looking for.

Not that every caller is in this situation! It runs the gamut: on one end is this (or even, as Amy writes, the ones who never call), and on the other end is someone calling to set up their appointment while also ordering dinner for five from the drive-through. But that's a story for another post.

Wednesday, February 29, 2012

Guest post: Caring for the Ones Who Never Call


I'm incredibly pleased to introduce a guest writer today. Amy Littlefield is a former abortion counselor and founder of The Provider Project: Stories From the Abortion-Providing Community, an excellent and groundbreaking endeavor that really strikes a chord with our own blog's founding mission.

Stay tuned to the Provider Project, where Amy's piece is cross-posted, and you might see an Abortioneers post there soon!


~~~~~~~~~~~~~~~~~~~~~~~~~~

Amy Littlefield

Caring for the Ones Who Never Call

It can be a scary prospect to call up an abortion clinic and make an appointment for what has become one of our society's most stigmatized -- and yet one of its most common -- medical procedures.

Which is probably why some patients don't immediately admit that's why they're calling.

As a former phone counselor at a clinic, I used to hear a lot of: "Um...I wanted to know how much it costs?" and "Hi...I'm looking for some information about...abortion?"

(This last one was spoken as a question, with the word "abortion" issued in a whisper, like a big, bad, ugly secret.)

I sometimes tried to use the word as much as possible when I answered those tentative calls.

"I would be happy to answer any questions you have about ABORTION! What type of ABORTION do you think you might be interested in having?"

Often, these patients weren’t simply calling for information; they knew they wanted an abortion, but they were scared and confused about what the process might entail.

I sometimes felt like women called just to test us out. Maybe they had always believed abortion was murder and they wanted to know whether we would tell them what they were doing was wrong or try to make them feel guilty. Maybe they were wondering whether the women who worked in the Big, Bad Baby-Killing Center were human beings like them. Many were scared they wouldn't be able to have children in the future, or that we would do something violent and terrible to remove their unwanted pregnancies.

They were certain we would judge them, just as others in their life had judged them. They were wondering whether they could trust us with their stories.

They ached to justify themselves.

"Look, I have to do this, I have a nine-month-old at home."

"I'm homeless and I already have two kids."

"I've never believed in abortion, but I just can't have a baby right now."

I was sometimes amazed at how relieved women were to tell their stories. To a stranger. Over the phone. And to have that stranger accept their stories Without judgment. Without telling them what was right and what was wrong. So listening became part of the process of making an appointment. When I finished booking the appointment and asked if they had any other questions, I could sometimes hear the relief in their voices.

Given how terrifying that first step can be for many patients, I often wondered how many women wanted to call, but never did.

The abortion rate has been declining among almost all groups of women across the country (although a recent study [pdf] showed that the global abortion rate has stalled after a period of decline). Many in the abortion-providing community believe this decline is a result of rising stigma, not of improved access to birth control or sex education (since, by and large, those things are not improving). Nor is it happening because women's economic situations have magically improved, since the abortion rate is still rising among poor women (which proves, by the way, that you can't advocate for reproductive justice without combating capitalist exploitation of the poor).

Brigit Ordway, a veteran counselor whom I interviewed as part of an audio project compiling voices from the abortion-providing community told me she thinks women face more stigma now than they did back in the decade or so after it was legalized.

She said:

"That's the biggest difference now -- women aren't telling each other about this. We all did and we got support, for the most part. Now, probably most women would get support from their friends and family, but they’re assuming that they won't. They're assuming that everybody is not pro-choice and that they're going to be judged and maybe even worse, you know, maybe somebody's going to come throw something at them. So women are silent about it now. They don't get the support of each other or society, because they don't talk about it, I think. It's a huge difference. It's all now secret and shameful for people."

So abortion counseling, for me, whether it was done on the phone or in person, became largely about trying to lift the burden of guilt that women thought they were obligated to feel for having an abortion. It was about helping them realize that they were still good, still loving, still worthy of respect. They drove past protesters and graphic posters of chopped-up babies to get into the clinic, but once they were inside, they were treated with respect.

Every so often we would get a call from a woman who wanted to come to the clinic, but couldn't bring herself to enter the doors after she saw the protesters' signs. Those women reminded me how limited my understanding of abortion is. I saw women who were beating themselves up emotionally for having an abortion they felt was necessary. But I never saw the women who were too scared to come in, too scared to even call.

One abortion provider whom I interviewed has found a way to help those women.

Dr. Deborah Oyer, who owns a clinic in Seattle, Washington, created a series of videos describing the process of an abortion at her clinic. In a soothing and straightforward voice, she describes the steps a patient goes through, from the moment she enters the door until she leaves. This is the kind of education I tried to do with patients over the phone -- but she has found a way to do it without requiring women to take that scary first step. Instead, wrapped in the Internet's comfy blanket of anonymity, they can learn that abortion is not as scary as they might have imagined.

The videos provide basic education about abortion and birth control that counteract common and harmful myths. They also show women that -- contrary to popular mythology -- the doctor who will be performing their abortion is a friendly and approachable woman, not a crazy, rabid devil-monster with horns (Oyer told me she often sees women relax visibly after she enters the room, since she is so un-monsterlike). She has one video that consists entirely of her introducing herself. That video, uploaded two years ago, has 550 views on YouTube.

The video about surgical abortion has 58,816.

The one on medication abortion has 27,668.

Clearly, people need this information.

I'm grateful to Deborah Oyer for putting her voice and face out there, despite the risks that it could mean for her in a world where abortion providers are targeted with hate speech and harassment, and even sometimes with bullets. I'm grateful that there is accurate information out there about abortion for everyone -- of every gender -- who wonders how it is done. But I’m especially grateful that there is education for the patients whom I never got to talk to -- for the ones who never call.

Listen to Deborah Oyer discussing the videos at The Provider Project, www.theproviderproject.org.

Monday, February 13, 2012

I had a relative in town all week...


...and I just have some questions for my fellow abortioneers.


Is this how it usually goes down for you?


Sub-questions:
  • Which one of you avoids bringing it up -- you or the relative(s)?
  • Which one of you subtly changes the subject?
  • Which one of you decides to end the conversation?
  • Which one of you lets the other person have the last word, and/or decides to leave it at "agreeing to disagree"?
...Or do you just have an all-out fight?
...Or is everything hunky-dory with all your relatives? (Congratulations!)

These aren't rhetorical questions, I'm just curious about the whole spectrum of experiences (from people I know personally, it's already quite broad). So tell me how it is for you.

Thursday, September 29, 2011

All stigma great and small

Gender Across Borders just hosted a fantastic series on stigma, including - shocker - abortion stigma. Stigma against providers as well as patients, perceived as well as anticipated, internalized as well as externally enforced. I'll probably be talking more about these things in the coming weeks.

But the thing I really want to talk about ASAP is this one: Pivotal Positions: Transforming Abortion Provider Stigma. Jennifer Colletti accurately depicts stigma against providers as the complex and diversely-manifested problem that it really is. It's not felt the same way or from the same sources in all places, and I think that's important to remember.

It's not hard for us, for abortioneers I mean, to rage against the full-blown anti-choice model of stigma: literally demonizing us and alleging Satanic rituals, stalking our children, calling providers murderers and those who provide any related care accomplices (or "killer-helpers," in the words of one persistent but not very inventive fellow). When we encounter people who do this, their failure to accept our personhood and the value of our lives (while insisting that those of the embryos are inalienable, I'll add) says to us that they don't care about how life might be lived by people other than themselves, meaning they're either oblivious and narcissistic or cruel and dictatorial. So we can easily write them off.

What's harder, though, is to talk about how our parents sidestep friends' questions about what their progeny are doing these days, or how high school reunions are at even greater risk of being depressing/distressing/disastrous than for everyone else, or how we worry about our kids learning what we do not because we aren't proud but because their classmates' parents might shame or punish them.

We go to schools that don't want to talk too much about abortion because some nebulous outside audience may object; we attend reproductive health lectures by professors who feel comfortable accommodating the opinion that it's OK to be anti-reproductive health; we don't get hired because someone thought we'd bring unnecessary attention to an organization that doesn't even really care about abortion either way, maybe they even support what we do, but just wants to get its own work done without pointless interference. You will never see an abortioneer nominated to the Department of Health and Human Services.

These things don't feel like stigmatizing incidents so much as the material that our lives' scenery is made out of. It's in the water, it's in the air. It feels like there's not as much to say about them, or else you're being melodramatic, compared to how fucked up it is to get shot down dead. But it's still stigma and it still harms our health and happiness.

We need the abortioneers around us to support us through crap like this; and we need non-abortioneers around us to get it. Make it your mission to let your on-the-fencey non-abortioneer acquaintances know what you deal with just for going to work.

Monday, September 12, 2011

What isn't about abortion?


Abortioneers. Tell me if you haven't met someone -- a young girl, an older woman, a mother of four, the grandmother of the patient, a survivor on the run -- whose hands you wanted to grasp as you told her, basically, this:


The Laughing Heart

your life is your life
don’t let it be clubbed into dank submission.
be on the watch.
there are ways out.
there is a light somewhere.
it may not be much light but
it beats the darkness.
be on the watch.
the gods will offer you chances.
know them.
take them.
you can’t beat death but
you can beat death in life, sometimes.
and the more often you learn to do it,
the more light there will be.
your life is your life.
know it while you have it.
you are marvelous
the gods wait to delight
in you.


Charles Bukowski

Wednesday, August 24, 2011

Please shut up so we can actually talk

Sometimes anti-abortion spokespeople act like it's huge news or a total outrage that abortion providers and abortion-rights advocates are hesitant to discuss flaws in their colleagues, partners, or movement. "See," the antis say -- and you can almost hear their crossed arms and satisfied smirk -- "They're only worried about protecting themselves, even if it means protecting their predatory, dangerous, greedy peers." And anti-abortion "activists" are constantly manufacturing problems to "investigate" and "expose" as well -- like when Lila Rose tries to prove that Planned Parenthood staff protect child traffickers, when actually they're telling the fake traffickers that young women can receive free checkups there (true), and then alerting the police (appropriate). 

In such an atmosphere, where tapes are heavily edited and even simple statements get twisted to mean something else entirely, is it any wonder that we fear perverse or disproportionate consequences, from antis and employers alike, if we speak up about the non-manufactured problems that do exist? 

Don't misunderstand: all of us, pro- and anti-choice, want dangerous abortion practices or abusive providers to be brought to light. But those are few and far between, way rarer than anti press would have us believe. So we have to spend our time dissecting what's real and what's BS, and meanwhile, there are more subtle issues that can't take stage, like "I prefer X style of abortion care provision while the only clinic in town provides it like Y," or "My organization has a fantastic mission but terrible leadership," and so forth. Stuff that I really want us to work on. Stuff that would move abortion care from "widely safe, usually decent, sometimes wonderful" to "uniformly excellent." 

I won't give a million more examples right now, but I'm working on it. But if, for example, you want to know why it's taken me weeks to draft (and months to conceptualize) a critique of Planned Parenthood's current position in our field, all you have to do is take a gander at shit like this: